
Why Chronic Inflammation Never Shuts Off: The Three Stages and Your Terrain
By Dr. John Bartemus, DC, CFMP, Functional Medicine Charlotte, PC. Published October 27, 2026.
If your inflammation keeps coming back no matter what you cut out of your diet, the problem is probably not the thing starting the fire. It is that your body has forgotten how to put it out. Most people, and most clinicians, picture inflammation as a switch: it is on, or it is off, and the job is to bring it down. A month of immunology research points to a more accurate and more useful picture, and it changes what you should actually be working on.
Short answer: Inflammation is not a switch. It is a process with a life cycle. It gets ignited, it gets amplified, and in a healthy body it gets actively shut down and cleaned up. Chronic disease is what happens when that life cycle breaks at one of its stages, most often not at ignition but at persistence or resolution. And whether a spark becomes a fire at all depends on the ground it lands on: your metabolism, your tissue, and your gut. That ground is called terrain, and unlike a diagnosis, terrain can be changed. That is root-cause philosophy in one picture.
Inflammation is a fire, not a light switch
Fire is the right teaching image, because it carries the whole process without jargon. A fire needs ignition. It needs fuel to spread and persist. And it needs a fire brigade to put it out and clear the debris. A house does not burn down only because a match was struck. It burns down because the match met dry conditions, the fire found fuel, and the brigade either never came or could not finish the job.
There is a second idea sitting underneath the first. Whether the immune system overreacts or stays calm is not decided by the immune cells alone. It is decided by the conditions those cells live in: their fuel, their metabolism, and the tissue around them. The scientific name for this is immunometabolism, the study of how a cell’s metabolic state determines how it behaves. The relationship runs both ways: metabolism shapes immune behavior, and inflammatory signals in turn reprogram a cell’s metabolism. This is why two people with the same diagnosis can need very different plans, and it ties immune health and metabolic health into one subject.
Stage one: ignition, and the ground it lands on
Inflammation starts when the immune system detects a threat, real or mistaken. Three findings from this period show how ignition works and why where it lands is not random.
A single metabolic protein can throw the switch. Researchers at Johns Hopkins identified a protein called human resistin as a driver that activates one of the body’s most powerful inflammatory pathways, the NLRP3 inflammasome (PLOS One, September 2026). Resistin comes out of metabolic and fat tissue, so this is a clean example of metabolism lighting the match on a pathway tied to cardiovascular disease, diabetes, and autoimmune disorders. Blocking resistin reduced the pathway in the lab, but this is a mechanism, not an available therapy.
Sometimes the alarm is false. Work from the Hebrew University of Jerusalem showed that in certain DNA-repair disorders, broken fragments of the body’s own DNA leak out and trip an immune sensor called cGAS, which mistakes them for a virus (Genes, September 2026). The sensor sounds an alarm against the body itself and keeps inflammation running long after any real threat is gone. This is sterile inflammation, and it sits at the center of autoimmunity and aging. Not all inflammation is a response to an outside invader. Some of it is the body misreading its own debris as an enemy.
Where the fire lands is built into the tissue. A study from Oxford found that vulnerability to rheumatoid arthritis may be set before birth (Nature Immunology, September 2026). The finger joints commonly attacked in rheumatoid arthritis carried more synovial tissue and more of a specific fibroblast population than the joints usually spared, and those differences were present before birth. The immune system did not decide on its own which joints to attack. The local tissue made some joints more combustible. That is terrain in its most literal form: it explains where disease lands, not what triggers it.
Stage two: why the fire keeps burning
If ignition were the whole story, inflammation would flare and fade. Chronic disease lives in the second stage, where the fire is amplified and sustained. This is the most important part of the thread for root-cause work, because this is where acute becomes chronic, and almost no one addresses it.
Zombie cells that keep smoldering. As we age, some cells stop dividing but refuse to die. These senescent cells, often called zombie cells, sit in tissue and release a steady stream of inflammatory signals. Researchers at Sanford Burnham Prebys and Mayo Clinic showed how they keep inflammation burning, and the mechanism runs through the mitochondria, the cell’s energy machinery, which unlocks inflammatory genes and leaks material the immune system reads as a danger signal (Nature, September 2026). A research compound reduced inflammation across multiple mouse tissues and improved healthspan. This is the clearest single illustration that metabolism inside a cell decides how inflammatory that cell becomes.
The fire brigade stops showing up. The body ends inflammation partly by having immune cells eat and clear worn-out cells. A Stanford study found that with age, the cleanup macrophages lose that ability, so inflammation-promoting cells pile up instead of being removed (Science, September 2026). Blocking the receptor responsible kept mouse organs youthful across many tissues. Part of why we age and inflame is not that we start too many fires, but that the brigade retires. A related October finding tied the brain’s resident immune cells to lost sleep in mice: calming overactive microglia restored more than two hours of sleep per day (Alzheimer’s and Dementia, October 2026).
Stage three: resolution is an active job, not an empty tank
Here is the idea that reframes everything. Inflammation does not end because it runs out of fuel. It ends because the body actively switches it off and cleans up. Resolution is its own program, with its own molecules and machinery. Once you understand this, the goal stops being only to suppress inflammation and starts to include asking whether the body’s off switch is working.
The body has built-in brakes. The strongest evidence in this period came from University College London, and it stands out because it was done in people (Nature Communications, September 2026). The researchers mapped a natural braking system built from fat-derived molecules called epoxy-oxylipins. In healthy volunteers given a short, harmless inflammatory challenge, a drug that raised these molecules helped pain resolve faster and sharply reduced the immune cells tied to persistent inflammation. The brake is real, it is measurable in humans, and it can be strengthened. This is an experimental drug in a small human study, with trials in rheumatoid arthritis and cardiovascular disease proposed, so the conceptual value today is higher than the clinical value: it proves resolution is an active, addressable program.
Diet can feed the brake, not only the fire. A University of Louisville study found that urolithin A, a compound gut bacteria make from pomegranates, walnuts, and berries, selectively activated a receptor in the gut lining and triggered an inflammasome in a protective mode that helped repair the barrier and strengthen defenses (Nature Communications, September 2026). It was confirmed in human inflammatory bowel disease tissue as well as cell and organoid models. The same inflammatory machinery can protect or harm depending on where it fires and how hard, and diet is one of the inputs that decides which. I covered this barrier-repair pathway and its cardiometabolic implications in more detail in my article on the gut barrier and cardiometabolic disease.
The layer underneath: the immune response is tuned by its terrain
Across every stage, one pattern repeats. Immune cells are not simply good or bad, calm or aggressive. They are tuned by the metabolic conditions they sit in. This is the part of the thread that most directly supports root-cause practice, because terrain is modifiable in ways a fixed diagnosis is not.
A nutrient can act as a dimmer switch. A Cincinnati Children’s study showed that the amino acid glutamine acts like a dimmer on inflammatory T cells in fatty liver disease (Cell Metabolism, September 2026). As glutamine inside those cells fell, they turned more inflammatory and the liver took more damage. Restoring it eased the inflammation. The researchers called glutamine metabolism a rheostat, a dimmer rather than an on-off switch. This was shown in human samples, organoids, and mice, and it is not an argument for taking glutamine supplements. It is proof that a cell’s fuel sets its behavior.
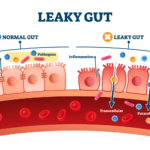
Same food, different gut. A University of North Carolina study found that oxalate, a compound in many healthy plant foods, may actively drive gut inflammation in inflammatory bowel disease, and the problem was not how much people ate but how their gut handled it (Cellular and Molecular Gastroenterology and Hepatology, September 2026). Affected guts under-expressed the transporters that move oxalate out and lacked the bacteria that degrade it. This is bio-individuality with a mechanism: terrain plus exposure, not exposure alone. It is one of the cleanest explanations for why blanket diet rules fail. The same logic shows up in lupus, where T cell metabolic reprogramming is now described as a driver (Frontiers in Immunology, October 2026). For the related question of why autoimmune conditions fall unevenly across people, see my article on why autoimmune disease affects women more, and for the barrier that sits upstream of much of this, my article on leaky gut.
What this means for root-cause care
The synthesis gives a clean framework to apply. When inflammation is chronic, ask which stage of the life cycle is broken, and ask what in the terrain is keeping it broken.
- Stop treating inflammation as a switch. Think of it as a life cycle with three stages: ignition, persistence, and resolution. Name the stage before naming a fix.
- Treat failed resolution as a primary target. Much chronic disease is a resolution failure, not an ignition excess. Supporting the body’s off switch is a different strategy than only suppressing the fire.
- Put terrain at the center. The same trigger lands differently depending on metabolism, tissue, and the microbiome. This is why two patients with the same diagnosis need different plans, and it is the strongest evidence-based case for individualized care.
- Use diet as a terrain input, both ways. Food can feed the fire (oxalate in the wrong gut) or feed the brake (urolithin A precursors from pomegranates, walnuts, and berries). The lever is the terrain, not the food in isolation.
- Keep metabolism and immunity in one frame. Resistin, glutamine, lipids, and senescent-cell mitochondria all say the same thing: metabolism sets immune behavior. Cardiometabolic health and immune health are one subject.
The honest limits
This thread deserves its evidence tier stated plainly, because that discipline is what separates careful work from hype. Most of these findings are mechanistic. Several are animal or cell studies, and several of the interventions are research compounds with no approved human use. The University College London brake study and parts of the glutamine and oxalate work reached human tissue or human volunteers, which is a higher tier, but none of this is a finished treatment to prescribe tomorrow. What is strong is the direction and the convergence: independent teams, in different diseases, using different methods, keep arriving at the same shape. Inflammation is a managed process, and the management is set by metabolic terrain. The individual mechanisms will be revised. The framework is holding.
Want the full version? The question of which stage is broken, and why, is exactly what my book The Autoimmune Answer walks through step by step. It is built to help you find what is keeping your own fire lit, rather than guessing. The Autoimmune Answer is available on Amazon.
Frequently asked questions
Why does chronic inflammation never shut off?
Usually not because the body cannot start inflammation, but because the fire keeps finding fuel or the system that ends it has broken down. Inflammation is ignited, amplified, and then actively shut down and cleaned up. Chronic inflammation is most often a failure of that shut-off and cleanup.
What are the three stages of chronic inflammation?
Ignition (the immune system detects a threat, real or mistaken), persistence (the fire is sustained by senescent cells and by cleanup cells that fail with age), and resolution (an active program that switches inflammation off). Chronic disease tends to live in persistence and resolution, not ignition.
What does “terrain” mean in inflammation?
The conditions immune cells live in: their fuel, metabolism, tissue, and microbiome. The field is immunometabolism. The same trigger acts differently depending on terrain, and terrain, unlike a diagnosis, can be changed.
Can diet affect how inflammation resolves?
There is mechanistic evidence that it can. Urolithin A, made by gut bacteria from pomegranates, walnuts, and berries, activated a protective repair mode in the gut lining, confirmed in human IBD tissue. It is food-first and mechanistically supported, not a proven cure.
Is all inflammation caused by an outside threat?
No. Some is a false alarm: the body’s own DNA fragments can trip the cGAS sensor, which keeps inflammation running with no real threat. This sterile inflammation is central to autoimmunity and aging.
About the author: Dr. John Bartemus, DC, CFMP, is a functional medicine practitioner, educator, speaker, and Amazon international number one best-selling author of The Autoimmune Answer, focusing on autoimmune disease, chronic inflammation, and root-cause medicine through Functional Medicine Charlotte, PC.
This article is for educational purposes only and is not medical advice. It synthesizes emerging research, much of it preclinical or early-stage, and is not a treatment protocol. Discuss any health or dietary changes with a qualified clinician.
References
- University of Oxford. “Rheumatoid arthritis joint vulnerability present before birth.” Nature Immunology, September 2026.
- Johns Hopkins Medicine. “Human resistin drives the NLRP3 inflammasome.” PLOS One, September 2026.
- Stanford Medicine. “Aging macrophages fail to clear neutrophils via the EP2 and PGE2 pathway.” Science, September 2026.
- University College London. “Epoxy-oxylipins as a natural resolution brake, measured in humans.” Nature Communications, September 2026.
- Sanford Burnham Prebys and Mayo Clinic. “Senescent-cell mitochondria sustain inflammation through the SASP.” Nature, September 2026.
- Hebrew University of Jerusalem. “cGAS false alarm and sterile inflammation in DNA-repair disorders.” Genes, September 2026.
- University of Louisville. “Urolithin A protectively activates gut NLRP6 and repairs the barrier.” Nature Communications, September 2026.
- PLOS Biology (revisited, September 2026). “The brain protein Menin restrains hypothalamic inflammation and declines with age.”
- Cincinnati Children’s. “Glutamine as a rheostat on inflammatory CD4 T cells in fatty liver disease.” Cell Metabolism, September 2026.
- University of North Carolina. “Oxalate handling and gut inflammation in IBD.” Cellular and Molecular Gastroenterology and Hepatology, September 2026.
- Frontiers in Immunology (October 2026). “T cell metabolic reprogramming in lupus; editorial on lipids as context-dependent immune regulators.”
- University of Kentucky. “Microglia-driven inflammation and sleep loss in mice.” Alzheimer’s and Dementia, October 2026.